Published on: 2026-10-08 | Written by: Dr. Mohamed Abdel Sattar, Professor of Kidney
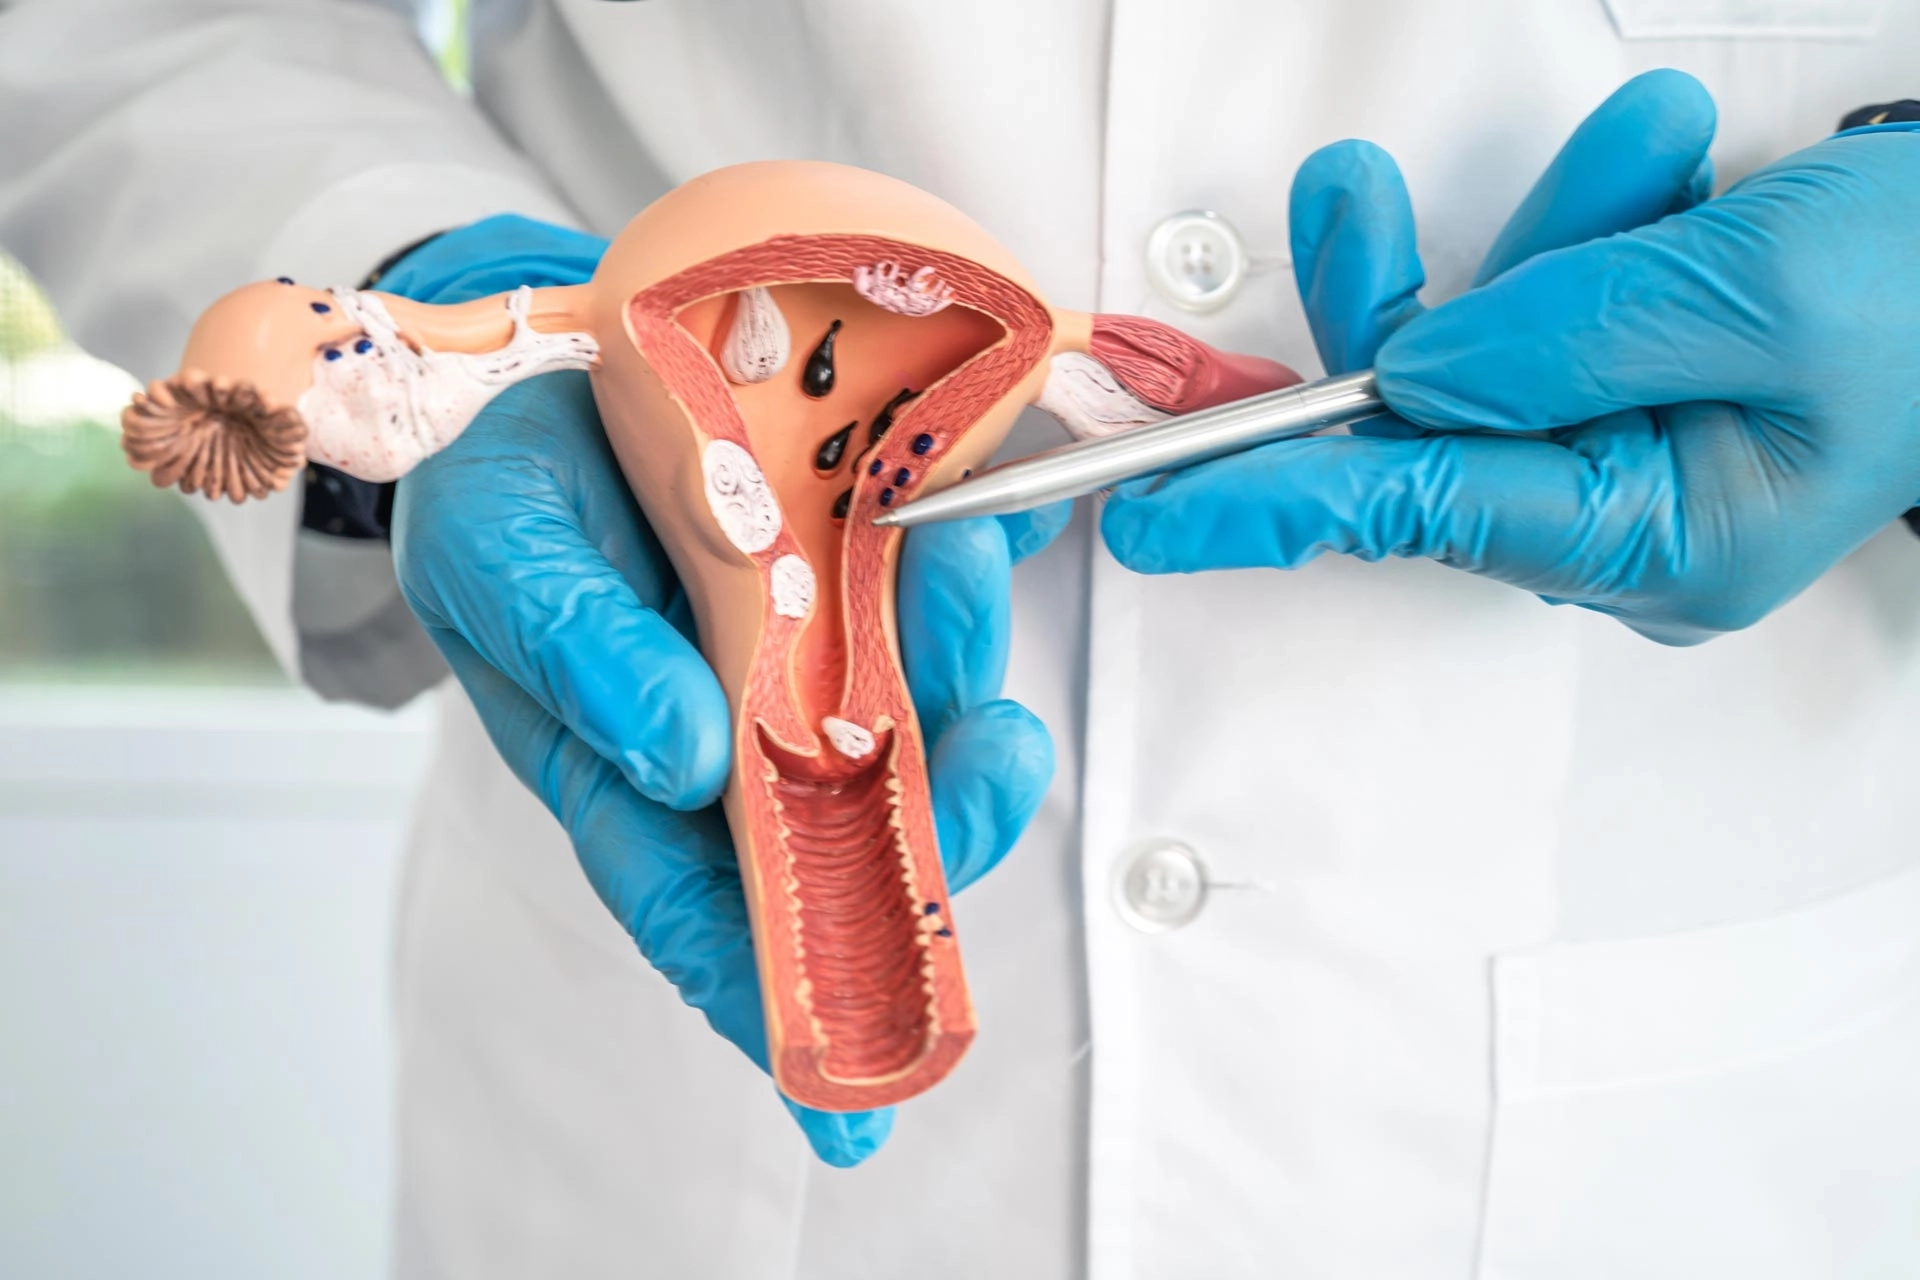
1. What Are Recurring Urinary Tract Infections and What Are Their Health Implications?
These infections typically arise when bacteria (most commonly Escherichia coli or E. coli) enter through the urethral opening and ascend into the bladder or kidneys, where they multiply and colonize the mucous membranes lining the urinary tract.
Dr. Mohamed Abdel Sattar clarifies that the continuous recurrence of infections does not merely signify a weakened immune system. In many cases, it points to a latent bacterial focus, partial urinary tract obstruction, or undetected small stones acting as fertile breeding grounds where bacteria hide and re-emerge after completing conventional antibiotic courses.
Medical Goals in Managing Recurrent Infections:
Complete Elimination of Bacterial Foci: Selecting the appropriate antibiotic based on urine culture and sensitivity testing.
Protecting the Kidneys from Bacterial Ascension: Preventing the spread of infection to the renal pelvis (pyelonephritis) and avoiding permanent renal scarring.
Restoring the Bladder's Protective Mucosa: Repairing the glycosaminoglycan (GAG) layer lining the bladder wall.
Improving Patient Quality of Life: Reducing persistent anxiety and chronic discomfort associated with micturition.
2. Causes and Risk Factors Leading to Recurrent Urinary Tract Infections
Causes range from anatomical and hormonal factors to daily behavioral habits that weaken the urinary defense system.
Dr. Mohamed Abdel Sattar points out that identifying the precise underlying cause of recurrence is the primary safety step. Etiologies in women (such as postmenopausal hormonal shifts or anatomical proximity) differ from those in men (such as prostatic enlargement or bladder calculi), requiring an individualized clinical assessment for each patient.
Primary Risk Factors and Causes:
Presence of Kidney or Bladder Stones: Stones serve as permanent bacterial reservoirs that are difficult for medications to penetrate effectively.
Incomplete Bladder Emptying: Post-void residual urine accumulation resulting from prostate enlargement or neurogenic bladder dysfunction.
Declining Estrogen Levels: Particularly in postmenopausal women, which reduces beneficial flora (Lactobacilli) and creates a dry, vulnerable tissue environment.
Anatomical Anomalies and Urinary Reflux: Such as vesicoureteral reflux (VUR), where urine flows backward from the bladder toward the kidneys.
Inadequate Fluid Intake and Delayed Voiding: Reducing the natural mechanical flushing of the bladder that occurs during regular urination.
3. Modern Treatment Approaches and Protocols
Modern management goes beyond prescribing quick, short-term antibiotics, relying instead on comprehensive, long-term, and preventive treatment strategies.
Dr. Mohamed Abdel Sattar advises the necessity of conducting a Urine Culture & Sensitivity test before initiating any pharmacological therapy, emphasizing that empirical, random antibiotic use without a culture leads to highly resistant bacterial strains, making future treatment far more complex.
Available Treatment Options and Protocols:
Targeted Antibiotic Therapy: Short, intensive antibiotic regimens administered upon symptom onset based on culture findings.
Low-Dose Prophylactic Therapy: Administering a very low daily dose of an appropriate antibiotic for 3 to 6 months to prevent bacterial adherence.
Topical Hormonal Therapy: Using local estrogen creams for postmenopausal women to enhance tissue health and support beneficial flora.
D-Mannose Supplements and Concentrated Cranberry Extract: Preventing E. coli bacteria from adhering to the bladder lining and facilitating their natural clearance.
Addressing Mechanical Causes: Surgical lithotripsy or managing prostate enlargement to eliminate urinary stasis.
4. Home Care Guidelines and Daily Habits to Prevent Relapse
Maintaining urinary health requires commitment to simple, healthy daily habits that safeguard against infection recurrence.
Dr. Mohamed Abdel Sattar stresses that drinking abundant amounts of water and voiding regularly represent the first and most active line of defense against infection, as continuous urine flow acts as a mechanical flush that washes away bacteria before they adhere to the bladder wall.
Daily Behavioral and Patient Care Recommendations:
Drink at Least 2.5 to 3 Liters of Water Daily: To stimulate diuresis and continually flush the urinary tract.
Do Not Hold Urine When Urging: Urinate every 2 to 3 hours at most to prevent urinary stasis.
Proper Personal Hygiene: Wipe from front to back to prevent transferring intestinal bacteria to the urethral opening.
Urinate Immediately After Intercourse: To flush out any bacteria that may have entered the urethra.
Avoid Perfumed Chemical Washes: To prevent irritating sensitive mucosal tissues and altering local pH balance.
5. Golden Rules for Monitoring and Preventing Complications
Periodic Urological Ultrasound Examinations: To confirm that the kidneys and bladder remain free of stones and urinary retention.
Repeat Urine Culture After Completing Treatment: To ensure complete eradication of the infection and rule out subclinical inflammation.
Prompt Attention to Early Relapse Signs: Such as severe burning, changes in urine color or odor, or flank pain.
Maintain Ongoing Follow-Ups with Your Specialist:
Dr. Mohamed Abdel Sattar emphasizes in his concluding advice that recurring urinary tract infections are not an incurable condition. Accurate diagnosis via urine cultures, addressing underlying root causes, and adhering to preventive guidelines guarantee long-term resolution, optimal urological health, and a comfortable life.